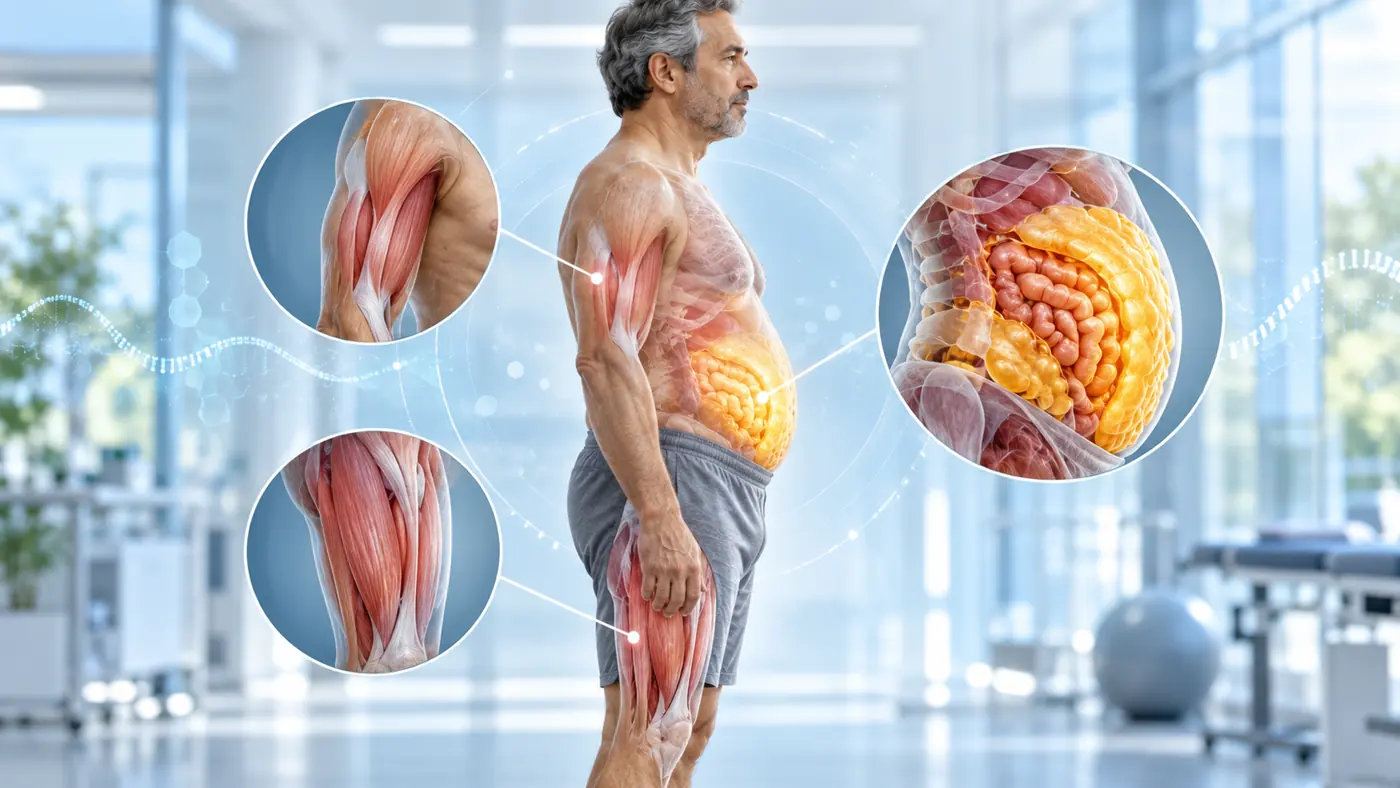
Sarcopenic obesity combines excess body fat with low muscle mass and strength. Learn its warning signs, diagnosis, risks, and evidence-based treatment.
A person can have excess body fat and still have too little functional muscle. This combination is called sarcopenic obesity. It matters because the scale may show a stable or high body weight while strength, mobility, metabolic health, and resilience are declining.
Sarcopenic obesity is not limited to very old adults. Ageing raises the risk, but physical inactivity, repeated restrictive dieting, chronic illness, inflammation, inadequate protein, and poorly planned weight loss can also contribute. It deserves particular attention when someone is losing weight with an anti-obesity medicine, recovering from illness, or finding everyday tasks unexpectedly difficult.
This guide explains what sarcopenic obesity means, how clinicians assess it, and how treatment can reduce fat while protecting or rebuilding muscle. It is educational and cannot diagnose an individual condition.
What is sarcopenic obesity?
The joint consensus from the European Society for Clinical Nutrition and Metabolism and the European Association for the Study of Obesity defines sarcopenic obesity as the coexistence of excess adiposity and low skeletal muscle mass accompanied by low muscle function. In practical terms, it is not simply having obesity and looking less muscular. Both body composition and muscle performance matter.
The ESPEN and EASO consensus statement recommends a structured process: identify people at risk, assess muscle function, assess body composition, and then consider whether related complications are present. This is important because body mass index alone cannot show how much weight is fat, muscle, fluid, or bone.
ABCD, or adiposity-based chronic disease, also looks beyond weight alone. The article on what adiposity-based chronic disease means explains why fat distribution, function, and complications are often more informative than a single BMI value.
Why high body fat and low muscle can occur together
Muscle and adipose tissue influence one another. Low activity reduces the stimulus that maintains muscle. Less muscle can lower physical capacity and make movement harder, which further reduces activity. Excess visceral fat may promote inflammation and insulin resistance, while insulin resistance can interfere with healthy muscle metabolism. This can become a self-reinforcing cycle.
Common contributors include:
- age-related changes in muscle protein synthesis and activity
- long periods of sitting or bed rest
- very low-calorie dieting without enough protein or resistance exercise
- repeated weight loss and regain
- type 2 diabetes, chronic kidney disease, heart disease, cancer, or inflammatory illness
- pain, arthritis, breathlessness, or neurological disease that limits movement
- poor appetite, dental problems, food insecurity, or an unbalanced diet
- medicines or treatments that affect appetite, hormones, or activity
Weight loss itself is not harmful when it is clinically appropriate and well planned. The concern is losing a disproportionate amount of lean tissue along with fat. A complete ABCD plan therefore considers muscle preservation alongside waist, glucose, blood pressure, liver health, sleep, and mobility.
Possible symptoms and warning signs
Sarcopenic obesity can be missed because body size may hide declining muscle. Some people have no obvious symptoms at first. Others notice reduced grip, slower walking, difficulty rising from a low chair, trouble carrying groceries, fatigue on stairs, poor balance, or a loss of confidence with everyday movement.
Warning signs worth discussing with a clinician include:
- unplanned weight loss or rapid weight cycling
- clothes becoming looser around the limbs while the waist remains similar
- difficulty standing from a chair without using the arms
- slower walking or repeated falls
- reduced strength after illness or hospitalisation
- substantial weight loss while taking a GLP-1 or another anti-obesity medicine
- persistent weakness despite adequate rest
Weakness can also result from anaemia, thyroid disease, vitamin deficiency, nerve or muscle disorders, infection, heart or lung disease, depression, or medication effects. A proper assessment should not assume that every symptom comes from body composition.
How sarcopenic obesity is diagnosed
There is no reliable home test and no single universal cut-off for every population. Clinicians combine history, function, examination, and body-composition information. Screening may start with age, recent weight change, chronic conditions, mobility, waist circumference, BMI, and a questionnaire about strength and falls.
Muscle function
Grip strength, chair-stand performance, and walking speed are common ways to assess function. A low result does not identify the cause by itself, but it signals that further evaluation may be useful. Function matters because a scan showing muscle tissue does not guarantee that the muscle performs well.
Body composition
Dual-energy X-ray absorptiometry and bioelectrical impedance analysis can estimate lean tissue and fat. Each method has limitations. Hydration, recent food or exercise, device equations, ethnicity, and the reference population can influence results. Measurements should be interpreted in context and preferably repeated under consistent conditions.
Read obesity diagnosis beyond BMI for a broader explanation of waist measurement, blood tests, and clinical complications.
Clinical stage and complications
The consensus framework separates sarcopenic obesity without related complications from disease accompanied by complications such as impaired mobility, metabolic disease, or disability. A clinician may also investigate glucose, lipids, liver and kidney function, thyroid status, nutrition, inflammation, and other causes based on the history.
Health risks associated with sarcopenic obesity
Low strength and excess adiposity can together affect more than appearance. Potential consequences include reduced mobility, falls, fractures, loss of independence, poorer recovery after illness or surgery, and greater cardiometabolic risk. Insulin resistance is especially relevant because skeletal muscle is a major site for glucose disposal.
The risk is individual. A label does not predict exactly what will happen to one person, and research definitions have varied. Still, identifying a decline early creates an opportunity to improve strength, food quality, and treatment planning before function deteriorates further.
Treatment: reduce harmful fat while protecting muscle
Treatment should address both parts of the condition. A plan focused only on a lower scale number can miss the central problem. Goals may include improved chair stands, walking capacity, grip, waist, glucose control, blood pressure, sleep, and quality of life.
Progressive resistance exercise
Resistance training provides the main signal for muscle to adapt. Depending on ability, this can include sit-to-stands, wall push-ups, resistance bands, machines, free weights, or supervised rehabilitation. Start with movements that can be performed safely and progress load or repetitions gradually.
Aerobic activity remains important for heart health, fitness, and energy balance. The practical guide to exercise for ABCD patients explains how strength, aerobic movement, and reduced sitting can work together.
Adequate protein and nutritional quality
Protein supports muscle repair, but the correct amount varies with age, kidney function, total intake, and clinical circumstances. Distributing protein-containing foods across meals may be more practical than relying on one large evening meal. Options include dal, beans, soy, tofu, eggs, fish, poultry, milk, curd, and suitable portions of paneer.
Protein supplements are not automatically necessary. People with kidney disease or other medical concerns need personalised advice. A dietitian can also help ensure that calorie reduction does not create deficiencies. See the diet strategies for ABCD management for a sustainable Indian meal framework.
Review weight-loss treatment
Anti-obesity medicines can produce meaningful health benefits when appropriately prescribed, but rapid loss, low food intake, nausea, and inactivity may raise concern about lean-tissue loss in some people. Do not stop or change a medicine without the prescriber. Instead, review the rate of loss, symptoms, protein intake, activity, and body-composition trend.
The guide to weight-loss medicines for ABCD explains who may benefit and why monitoring is part of treatment.
A practical weekly plan
- Complete two or three appropriately designed resistance sessions.
- Walk or perform another aerobic activity at a level suited to current health.
- Break up long sitting periods during the day.
- Include a suitable protein source in each main meal.
- Track strength or function as well as weight and waist.
- Review pain, balance, medicines, and nutrition with the relevant professional.
People who are frail, have repeated falls, severe joint pain, uncontrolled heart or lung disease, or have recently been hospitalised should seek professional guidance before starting an unsupervised programme.
Frequently asked questions
Can you have sarcopenic obesity with a normal BMI?
It is possible to have relatively high body fat and low muscle without a very high BMI. BMI cannot separate fat from lean tissue. Diagnosis still requires clinical assessment rather than appearance or a consumer scale alone.
Is sarcopenic obesity the same as being overweight and unfit?
No. Fitness can vary at any body size. Sarcopenic obesity specifically concerns excess adiposity together with low muscle mass and impaired muscle function, assessed using appropriate methods.
Can sarcopenic obesity be reversed?
Muscle strength and function can often improve with progressive training, adequate nutrition, treatment of contributing illness, and safe fat loss. The extent of improvement depends on age, disease, disability, adherence, and the cause.
Do GLP-1 medicines cause muscle loss?
Weight loss usually includes some lean tissue as well as fat, regardless of method. The clinical question is whether muscle loss is excessive and whether strength is declining. Resistance exercise, adequate nutrition, and medical monitoring are therefore important during treatment.
Which test is best for sarcopenic obesity?
No single test is sufficient. A useful assessment combines muscle function, body composition, symptoms, and complications. DXA and validated BIA can estimate body composition, while grip or chair-stand testing helps assess performance.
When should I see a doctor?
Arrange a review for unexplained weakness, rapid or unplanned weight loss, repeated falls, difficulty with routine movement, or declining strength during weight treatment. Sudden weakness, facial droop, speech difficulty, severe breathlessness, or chest pain requires urgent care.
Protect function, not just a number on the scale
Sarcopenic obesity shows why body weight alone cannot define metabolic health. The best plan aims to reduce harmful adiposity while preserving strength, mobility, and nutritional adequacy. If your weight is changing but your function is worsening, ask for an assessment that looks at muscle performance and body composition, not only BMI.
Medical disclaimer: This article provides general education and is not a diagnosis or personalised treatment plan. Consult a qualified healthcare professional for individual assessment.