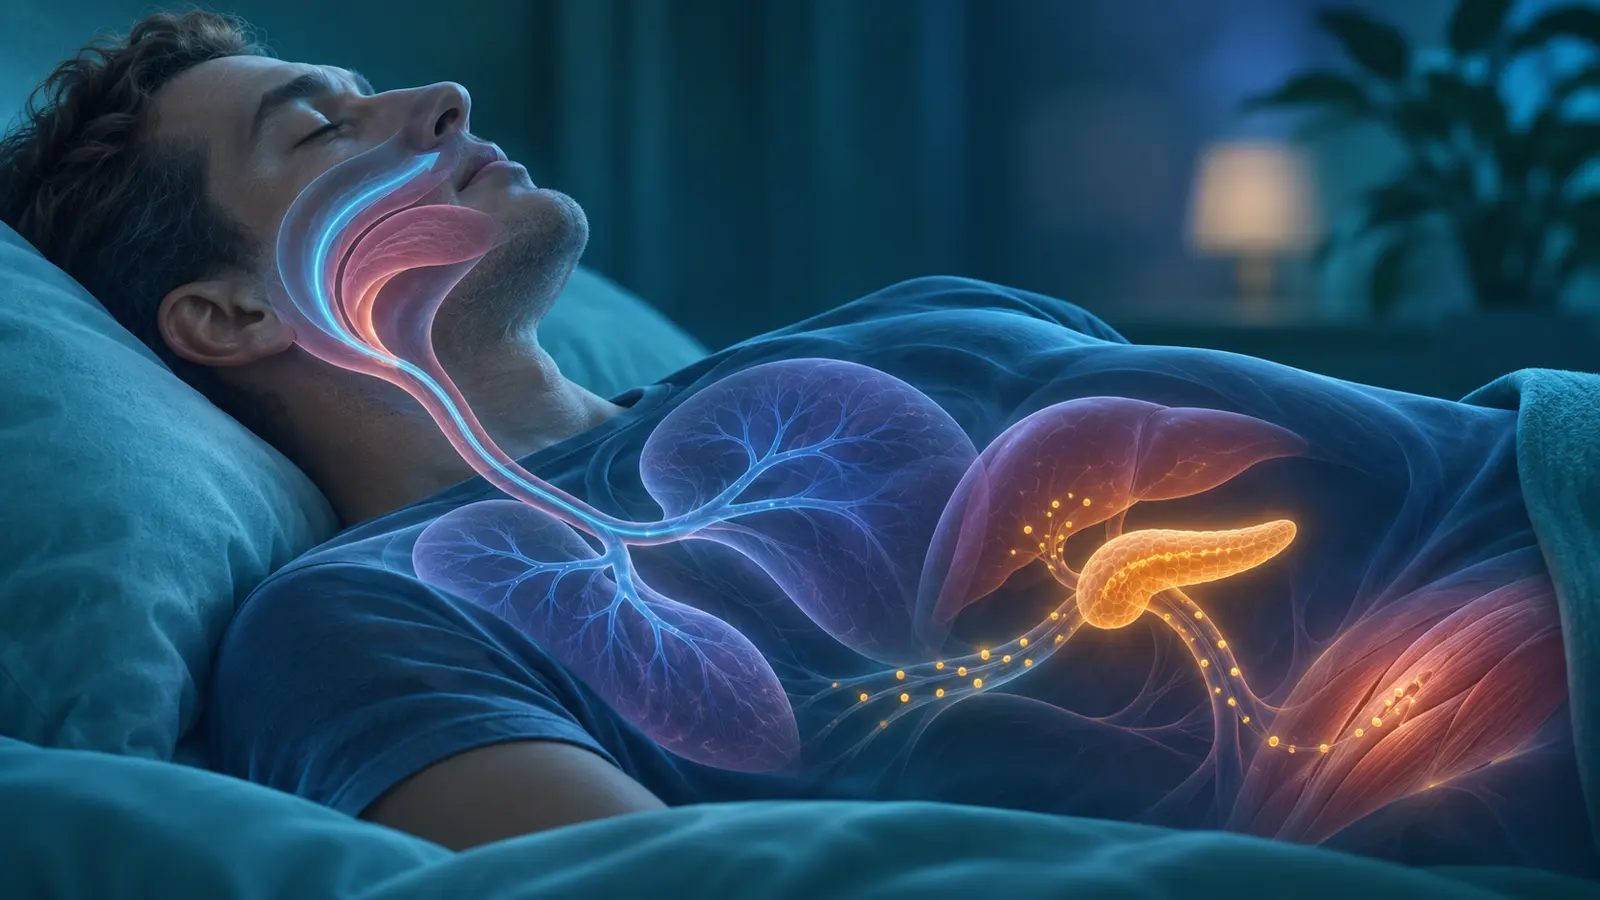
Explore how obstructive sleep apnea relates to insulin resistance, signs to notice, testing, and treatment limits.
Sleep Apnea and Insulin Resistance: The Link
Obstructive sleep apnea causes repeated narrowing or closure of the upper airway during sleep. Breathing pauses can fragment sleep and cause oxygen levels to fluctuate. The condition is associated with insulin resistance, type 2 diabetes and cardiovascular risk. That connection matters for metabolic health, but it does not mean every person with insulin resistance has sleep apnea or that treating apnea alone reverses diabetes.
This article focuses on a question often missed in weight discussions: could disturbed breathing at night be contributing to poor daytime energy and metabolic risk? Our ABCD and sleep apnea overview explains the broader relationship with adiposity. Here we focus on symptoms, testing and how to interpret the insulin-resistance connection.
What happens during obstructive sleep apnea?
The muscles around the upper airway relax during sleep. In susceptible people, the airway narrows repeatedly enough to reduce or stop airflow. The brain responds with brief arousals that reopen it. A person may not remember these events, yet sleep can be less restorative. Snoring is common but not universal, and snoring alone does not establish a diagnosis.
Body fat distribution can affect airway anatomy, but weight is not the only factor. Jaw structure, nasal obstruction, age, medications and other conditions may contribute. People at a normal BMI can have sleep apnea. Treating it as a simple consequence of excess weight may delay diagnosis in those who do not fit a stereotype. An assessment should follow symptoms and risk, not appearance alone.
Why is insulin resistance discussed?
Sleep fragmentation and intermittent low oxygen may affect stress responses, inflammation, appetite regulation and glucose handling. These are plausible pathways linking sleep apnea with insulin resistance. Research also has to account for shared factors such as adiposity and age. An association does not prove that apnea caused an individual person's abnormal glucose result.
The connection is clinically useful because both conditions can coexist and compound risk. A person with type 2 diabetes and persistent snoring or sleepiness should not have the sleep problem ignored. Similarly, a person diagnosed with sleep apnea may benefit from routine assessment of blood pressure and metabolic risk. Our insulin resistance before prediabetes guide describes why glucose may remain in range while metabolic risk develops.
Which symptoms should you notice?
Common clues are loud habitual snoring, witnessed pauses in breathing, gasping or choking at night, unrefreshing sleep, morning headache, dry mouth and daytime sleepiness. Some people report concentration problems or waking to urinate. Symptoms vary, and a bed partner may notice breathing events before the patient does. Women and older adults may describe fatigue or insomnia rather than dramatic snoring.
Daytime sleepiness matters for safety, especially while driving. If you are struggling to remain awake at the wheel, do not wait for a routine wellness appointment. Speak to a healthcare professional promptly and avoid driving when sleepy. A home watch or phone app cannot reliably rule out sleep apnea, even if it reports a high sleep score.
How is sleep apnea tested?
A clinician reviews symptoms, medical history, medicines and examination findings. Depending on the situation, they may recommend a home sleep apnea test or an overnight laboratory study. The right test depends on other illnesses, the likelihood of apnea and whether a different sleep disorder is possible. A negative home test may not end the evaluation if symptoms remain convincing.
The report often includes an apnea-hypopnea index or a similar measure of breathing events, alongside oxygen and sleep information. A single severity label does not capture all clinical impact. The doctor should relate the findings to symptoms, blood pressure, cardiovascular history and treatment goals. Do not diagnose yourself from the oxygen graph on a consumer device.
Does CPAP improve insulin resistance?
Continuous positive airway pressure, or CPAP, keeps the airway open during sleep for many patients. It can improve breathing events and daytime symptoms when used effectively. Studies of glucose or insulin outcomes have mixed results, partly because duration of use, baseline risk and study methods differ. It is not accurate to promise that CPAP alone will normalize glucose or make weight loss automatic.
If CPAP is prescribed, fit, comfort, regular use and follow-up matter. Tell the care team about mask leaks, dry mouth or difficulty tolerating the device rather than abandoning it silently. Other options may include oral appliances or selected procedures, depending on the patient's anatomy and severity. Treatment selection belongs with a qualified sleep clinician.
Weight loss and apnea can influence each other
For some people with excess adiposity, sustained weight loss reduces sleep apnea severity. Yet it may not eliminate the condition, and a repeat assessment may be needed before changing treatment. Poor sleep can also make appetite and activity plans harder to follow. This creates a practical two-way challenge, not a reason to blame the patient for either condition.
A metabolic plan may include nutrition, activity, strength training and treatment of related conditions. Monitor more than scale weight: waist circumference, blood pressure, HbA1c or fasting glucose when indicated, lipids, energy and sleep symptoms can matter. Our body composition guide discusses why fat distribution and muscle deserve attention.
What can you do while awaiting assessment?
Keep a record of symptoms, bed and wake times, and any witnessed pauses. Avoid alcohol close to bedtime if it worsens snoring, and discuss sedating medicines with the prescriber. Some people find side sleeping helps, but it is not a substitute for assessment when apnea is suspected. Do not buy a CPAP machine and set pressures yourself based on a phone app.
If you have diabetes, continue your prescribed care while sleep is being evaluated. Do not stop medicines because you expect apnea treatment to fix glucose. A coordinated plan can address both conditions and cardiovascular risk factors. The American Diabetes Association consensus report on sleep health discusses sleep in diabetes care, including the need to assess disorders rather than only sleep duration.
Why this matters for ABCD
Adiposity-based chronic disease looks beyond BMI at complications of excess or dysfunctional adiposity. Sleep apnea is one possible complication, and insulin resistance is another. Evaluating both can clarify a patient's overall risk and help set priorities. A person with normal blood sugar today can still have a clinically important sleep disorder. Conversely, an elevated glucose result needs its own assessment even if sleep apnea is found.
This approach avoids reducing health to one number. The question is not whether apnea “caused” all metabolic problems. It is whether recognizing and treating it improves symptoms, safety and risk management. Ask the clinician what results will be tracked and when treatment should be reviewed.
Frequently asked questions
Does snoring mean I have insulin resistance?
No. Snoring can occur without apnea, and it cannot diagnose insulin resistance. Persistent loud snoring with breathing pauses or daytime sleepiness warrants a sleep assessment.
Can a thin person have sleep apnea?
Yes. Airway anatomy and other factors matter. Normal BMI does not rule it out.
Will CPAP cure diabetes?
No. CPAP treats obstructive breathing during sleep. Glucose care and other risk-factor management may still be needed.
Is a smartwatch oxygen reading enough to diagnose apnea?
No. Consumer devices cannot replace a clinically selected sleep test and interpretation.
If I lose weight, can I stop CPAP?
Do not stop it without discussing symptoms and a reassessment with your sleep clinician. Apnea may persist after weight loss.
Which doctor should I see?
Start with a physician who can assess your sleep and metabolic history and refer you to a sleep specialist when indicated.