A lipid report can say your LDL cholesterol is within a target range while your clinician still worries about cardiovascular risk. One reason is that LDL cholesterol measures how much cholesterol is carried in LDL particles, while apolipopr
ApoB vs LDL Cholesterol: Which Test Adds More Insight?
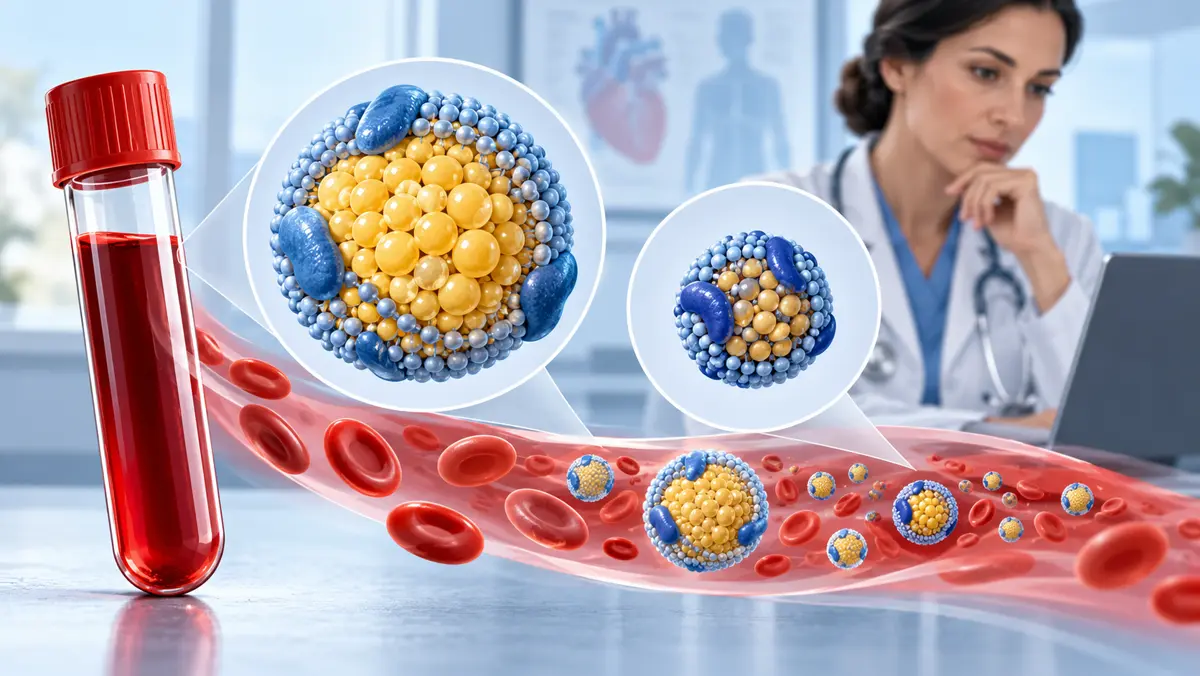
A lipid report can say your LDL cholesterol is within a target range while your clinician still worries about cardiovascular risk. One reason is that LDL cholesterol measures how much cholesterol is carried in LDL particles, while apolipoprotein B, or ApoB, provides an estimate of the number of atherogenic particles. Those are related but not identical questions. In people with high triglycerides, diabetes, or other metabolic problems, the two results can disagree in a clinically important way.
This article explains the difference without claiming that everyone needs a new test. It also reflects the 2026 US dyslipidemia guidance, which recommends selective ApoB measurement to refine risk assessment in certain circumstances. Your own decision should be made with a qualified clinician using your complete health history and locally applicable guidance.
What does LDL cholesterol measure?
LDL-C is the amount of cholesterol carried by low-density lipoprotein particles in a blood sample. It is a familiar part of a standard lipid profile and remains central to cardiovascular prevention and treatment decisions. Lowering LDL-C is an established way to reduce atherosclerotic cardiovascular risk in appropriately selected people. A result should be interpreted with age, blood pressure, smoking, diabetes, family history, and any previous cardiovascular disease.
LDL-C is not a count of particles. Imagine two delivery fleets carrying the same total amount of cargo. One fleet may have fewer heavily loaded vehicles; the other may have more lightly loaded vehicles. The total cargo is similar, but the number of vehicles differs. This analogy is imperfect, but it helps explain why LDL-C and ApoB can be discordant. The number of particles interacting with the artery wall may matter even when the cholesterol mass looks reassuring.
Standard lipid profiles also include HDL cholesterol and triglycerides. Non-HDL cholesterol, calculated by subtracting HDL-C from total cholesterol, captures cholesterol in several atherogenic particle types. A clinician may use these available measures before deciding whether ApoB will change management. More testing is useful only when it clarifies a real decision.
What does ApoB measure?
ApoB is a protein on atherogenic lipoprotein particles, including LDL and several triglyceride-rich particles. Each such particle carries one ApoB molecule, so a blood ApoB result approximates the number of these particles. It is not simply a different name for LDL-C. When particles carry less cholesterol each, ApoB may be higher than expected from LDL-C.
The American Heart Association explains that ApoB can add information when a standard cholesterol panel may underestimate risk. The 2026 multidisciplinary dyslipidemia guideline highlights situations such as elevated triglycerides, diabetes, or a low achieved LDL-C where ApoB may help assess residual risk and guide a clinician's decisions. This does not mean every adult should order ApoB at every checkup or change medication based on one result.
Our article on high triglycerides despite normal LDL explains one common pattern that prompts a broader metabolic assessment. ApoB may be one additional piece, but triglycerides, glucose, waist measurements, and the clinical history still need attention.
Why can metabolic dysfunction create a mismatch?
Insulin resistance and abdominal adiposity can accompany elevated triglycerides and changes in lipoprotein composition. A person may therefore have many cholesterol-poor atherogenic particles while LDL-C alone appears less concerning. The size of a particle is not the only issue; the overall number and lifetime exposure matter. Avoid interpreting one lipid marker as a complete picture of metabolic health.
ABCD, or adiposity-based chronic disease, asks clinicians to look beyond body mass index when assessing complications. Our guide to obesity diagnosis beyond BMI explains how waist circumference and blood tests can add context. A person at a normal BMI may still have metabolic risk, while a person at a higher BMI may have a different pattern. ApoB can be relevant to the cardiovascular side of that assessment, but it does not diagnose ABCD by itself.
The mismatch is also possible in the other direction. If results seem inconsistent, verify the laboratory method, treatment status, and whether a recent illness or major diet change could have influenced testing. Your clinician may use non-HDL-C, ApoB, Lp(a), or other information selectively rather than ordering every available marker at once.
Who might discuss ApoB testing?
People with high triglycerides, type 2 diabetes, established cardiovascular disease, metabolic syndrome, or a concern that LDL-C does not reflect their overall risk may have a reason to discuss ApoB. It may also help when decisions remain uncertain after a standard risk review. The 2026 guideline specifically notes that ApoB can refine risk assessment and guide therapy once LDL-C and non-HDL-C goals are met in selected higher-risk groups.
That statement should not be turned into a blanket screening recommendation for everyone. If you have no known risk factors and your standard assessment is clear, the result may not change your care. Conversely, if you have known heart disease or diabetes, a clinician may already have a strong reason to treat risk even without ApoB. Testing should support a decision, not delay evidence-based treatment.
Lipoprotein(a), written Lp(a), is a different marker from ApoB. The 2026 guidance recommends Lp(a) testing at least once in adulthood because inherited elevation can affect lifetime risk. Do not confuse the two or assume one replaces the other. Ask your clinician which question each test would answer for you.
How should you interpret a result?
Avoid reading ApoB against an online threshold without your risk category. A person with prior cardiovascular disease may have a different treatment goal from someone being assessed for primary prevention. Laboratories and guidelines may present ranges in different units or contexts. Your clinician should consider the result alongside LDL-C, non-HDL-C, triglycerides, blood pressure, glucose, medicines, family history, and any known vascular disease.
If ApoB is higher than expected, do not start or stop medication on your own. The next step may be to review adherence to an existing plan, nutrition, physical activity, tobacco exposure, or whether treatment needs adjustment. If you are not taking a lipid-lowering medicine, a shared decision considers absolute cardiovascular risk and preferences, not a single biomarker in isolation.
Our guide to high fasting insulin with normal blood sugar shows why apparently normal headline numbers sometimes need context. The same principle applies here: a test earns its place when it changes understanding and leads to a clear, appropriate action.
What actions matter whichever test you use?
Nutrition that emphasizes minimally processed foods, adequate fibre, and appropriate energy intake can support cardiometabolic health. Regular physical activity, muscle-strengthening work, smoking cessation, and blood-pressure management remain important. The exact plan should fit your health conditions and treatment goals. A favorable ApoB result does not erase the need for these habits, while an unfavorable result is not a reason for panic.
If medication is indicated, lifestyle actions and medication are partners rather than competitors. Discuss benefits, adverse effects, follow-up testing, and the rationale for any change with your treating professional. A repeat test may be useful after a treatment change, but the interval should be chosen for the decision being made. Repeating multiple biomarkers every few weeks without a plan may add confusion.
The best result of an ApoB discussion is not necessarily another test. It is a clearer understanding of your cardiovascular risk and what you will do next. For some people ApoB supplies that clarity; for others the standard profile and clinical history already answer the question.
Frequently asked questions
Is ApoB better than LDL cholesterol for everyone?
No single test replaces the whole risk assessment. LDL-C remains important. ApoB may add useful particle-number information in selected situations, especially when LDL-C may underestimate risk.
Can LDL be normal while ApoB is high?
Yes. The cholesterol carried by particles and the number of particles can differ. This mismatch is more likely in some metabolic patterns, including elevated triglycerides or diabetes.
Does a high ApoB mean I need a statin?
Not automatically. Treatment decisions depend on overall cardiovascular risk, medical history, other lipid measures, and clinician-patient discussion. Do not start or stop medication from one number alone.
Is ApoB the same as Lp(a)?
No. ApoB estimates atherogenic particle number. Lp(a) is a distinct inherited lipoprotein-related risk marker. They answer different questions and neither substitutes for a full assessment.
Should I request ApoB at every health checkup?
Usually not. Ask whether it would change your treatment or risk assessment. If the answer is unclear, a clinician may prioritize standard lipids and other established risks first.
Sources and medical note
This article follows the 2026 AHA multidisciplinary dyslipidemia guideline summary and AHA patient information on ApoB. It is educational information, not individualized medical or medication advice.