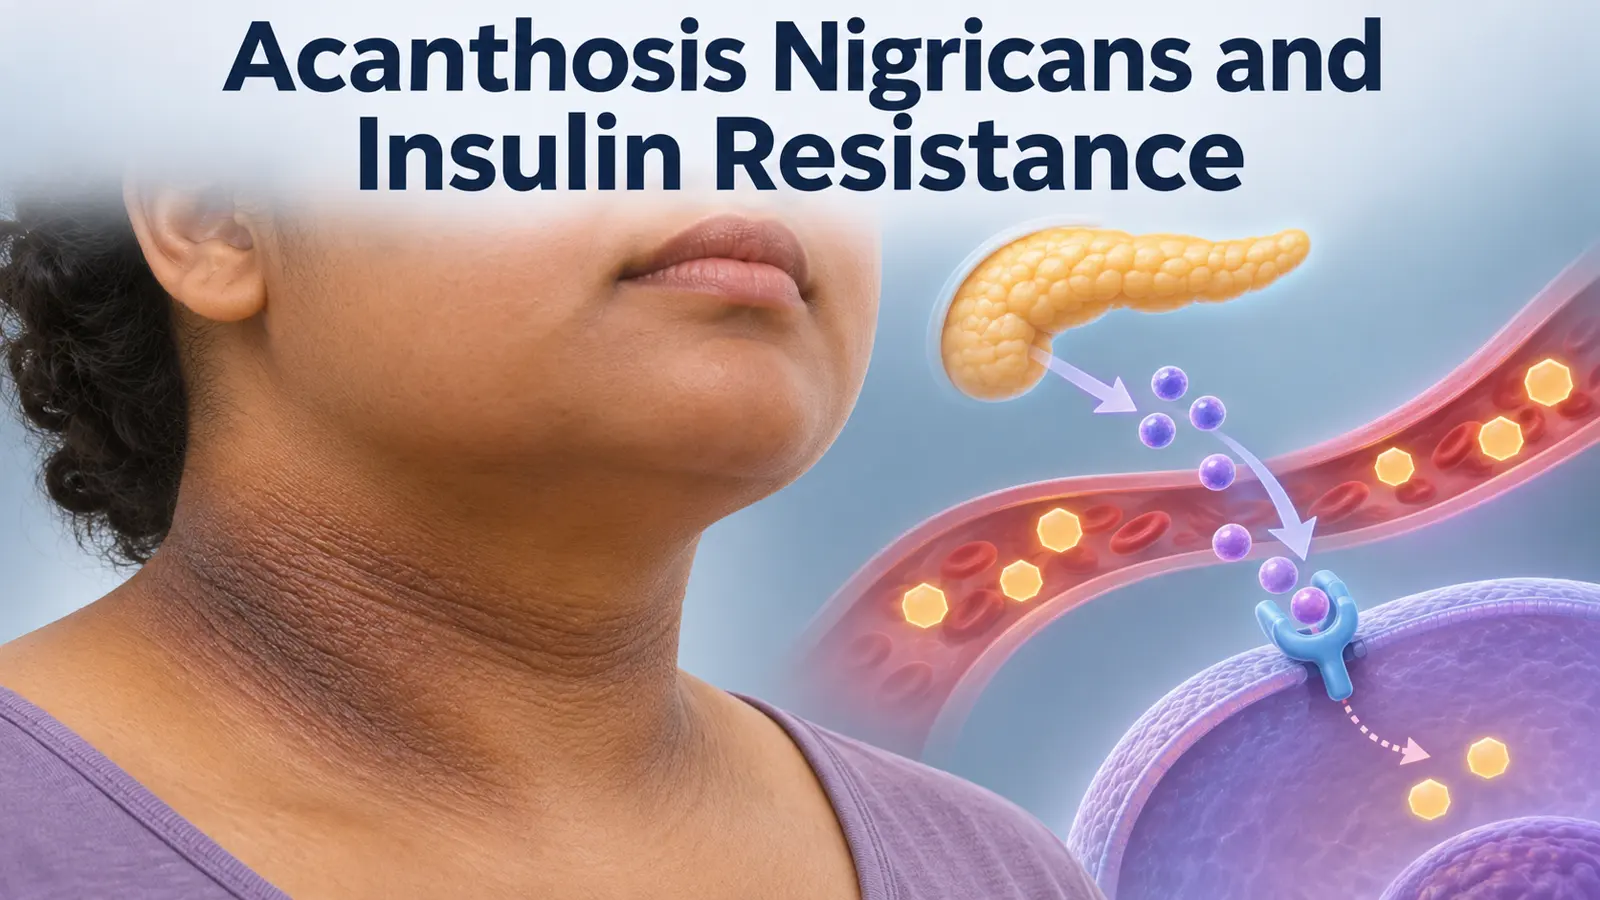
Understand acanthosis nigricans, its link with insulin resistance, other causes, screening questions and skin-care limits.
Acanthosis Nigricans and Insulin Resistance
Dark, velvety-looking patches around the neck, armpits or groin can be acanthosis nigricans. People sometimes mistake them for dirt and scrub harder, but the discoloration is not a hygiene problem. The finding can be associated with insulin resistance and may prompt screening for prediabetes or diabetes. It can also have other causes, and a photograph cannot confirm the diagnosis. The right response is a clinical assessment of the skin and broader metabolic risk.
This article focuses on the visible skin sign and the questions it raises. Our insulin-resistance symptoms guide covers the wider symptom picture, while our high fasting insulin article addresses a laboratory result. These are related but distinct search intents.
What does acanthosis nigricans look like?
Patches often appear darker and thicker than surrounding skin, with a soft or velvety texture. They commonly occur in skin folds, especially the back or sides of the neck, armpits and groin. The appearance can vary across skin tones. Some people notice skin tags nearby. It may develop gradually and be painless, although irritation or itching can occur.
The American Academy of Dermatology explains that acanthosis nigricans has several possible causes. Other skin conditions, friction, fungal problems or post-inflammatory pigmentation can look similar. A dermatologist or physician can examine the texture and distribution rather than assuming every dark patch is a metabolic sign.
How is it connected to insulin resistance?
Insulin resistance means the body's cells respond less effectively to insulin, so the pancreas may produce more to keep blood sugar controlled. Higher circulating insulin is thought to stimulate growth pathways in the skin that contribute to the characteristic thickening. The American Diabetes Association describes acanthosis nigricans as common in people with insulin resistance, prediabetes or type 2 diabetes.
The skin sign is a clue, not a direct measurement of insulin action. Some people with insulin resistance do not have acanthosis nigricans, and some people with the skin finding have a different cause. A normal fasting glucose on one day does not settle every question, but it also does not mean that an extensive hormone panel is automatically needed.
Who is more likely to develop it?
Excess adiposity, especially with metabolic risk, is a common association. Family history, certain hormonal conditions such as PCOS and some medicines can also contribute. The condition can appear in children or adults. A person at normal BMI can still have the sign, so weight alone should not decide whether the skin deserves evaluation.
Rarely, sudden or widespread acanthosis nigricans in an adult can accompany a more serious condition. The dermatologist's assessment is particularly important when onset is rapid, the pattern is unusual, or there are other concerning symptoms. Most cases are not cancer, and a reader should not assume the worst from a picture online. The clinical history guides next steps.
Does it mean I already have diabetes?
No. It can occur before blood glucose crosses a diagnostic threshold, and it can occur without diabetes. A clinician may consider HbA1c or fasting glucose based on age, family history, waist, blood pressure and other factors. Some people may need additional evaluation if results and symptoms do not match. The purpose is to identify risk early and plan appropriate follow-up.
Do not diagnose diabetes from a skin patch or rule it out because you feel well. Type 2 diabetes can be asymptomatic. Our insulin resistance before prediabetes guide explains how metabolic dysfunction can precede a clear glucose abnormality. That concept should prompt thoughtful assessment, not repeated unvalidated testing.
What other conditions should be considered?
PCOS can coexist with insulin resistance and acanthosis nigricans. Medication history matters because certain drugs can be associated with the finding. Endocrine disorders may be considered when other signs point toward them. A clinician may ask about menstrual changes, weight trajectory, family history and other symptoms. The skin pattern itself can also help distinguish acanthosis nigricans from other pigmentation.
There is no single standard panel appropriate for every patient. Testing should follow a clinical question. Our PCOS and insulin resistance guide discusses the metabolic context for that group. A person without PCOS should not assume the same investigation applies.
Can the patches be scrubbed away?
No. Aggressive scrubbing, bleaching or strong acids can irritate skin and worsen pigmentation. The first step is confirming the diagnosis and addressing any underlying cause. A dermatologist may recommend a skin treatment for texture or appearance, but cosmetic treatment alone does not evaluate metabolic risk. Products sold as instant cures should be treated cautiously.
Use gentle skin care while arranging an assessment. If a patch is painful, broken, bleeding or changing rapidly, seek review sooner. Do not use prescription creams from another person's treatment plan. Skin thickness and location can affect what is safe to apply.
What helps if insulin resistance is present?
Regular physical activity, strength training, adequate sleep and a sustainable dietary pattern can support metabolic health. For some people with excess adiposity, weight reduction can improve insulin resistance and the skin finding over time. Results vary, and the patch may not disappear completely or quickly. A clinician may recommend medicines for diabetes, PCOS or another condition when appropriate.
The goal is improving health markers and function, not punishing the body for a visible sign. Our natural ways to improve insulin sensitivity outlines practical habits. Do not stop medical treatment because lifestyle changes are underway. If you are a child or adolescent, family-focused care and appropriate pediatric assessment are especially important.
How does this fit the ABCD framework?
Adiposity-based chronic disease asks whether adiposity is causing or contributing to health complications rather than judging by BMI alone. Acanthosis nigricans may be one visible signal that a broader metabolic review is warranted. It is not itself a stage of ABCD, and it does not prove that adiposity is the only cause. Blood pressure, lipids, glucose, waist and other conditions may matter.
A good care plan combines the skin diagnosis with the person's risk factors, symptoms and preferences. Some people need only basic screening and follow-up; others need more extensive evaluation. Avoid creating a fixed treatment promise based on whether the skin lightens. Metabolic improvements may occur before visible changes.
When should you make an appointment?
Arrange a medical or dermatology assessment for new, persistent velvety darkening in a skin fold, particularly if you also have a family history of diabetes or other risk factors. Seek earlier assessment if the change is rapid, widespread or accompanied by weight loss, abdominal symptoms or other concerning changes. The clinician can confirm whether it is acanthosis nigricans and decide what screening is useful.
Bring a list of medicines and recent blood results. A photo showing how the patch changed over time may help. The appointment should lead to a clear plan for skin care, metabolic evaluation and follow-up, not just an isolated cream prescription.
Frequently asked questions
Is a dark neck always insulin resistance?
No. Several skin conditions can cause darkening. The velvety texture and distribution can be clues, but a clinician should examine it.
Does acanthosis nigricans mean diabetes?
No. It can be associated with insulin resistance or prediabetes, and other causes exist. Screening depends on the whole risk picture.
Can normal blood sugar rule out insulin resistance?
Not entirely. Glucose can remain in range for a time. A clinician decides whether follow-up is needed.
Will weight loss always clear the skin?
It can help some people, but improvement varies and may be slow. Treat underlying risk and discuss skin-specific options separately.
Should I use a bleaching cream?
Do not self-treat with strong products. Irritation can worsen pigmentation. Confirm the diagnosis and seek safe advice.
Can children develop it?
Yes. A pediatric clinician can assess metabolic risk and other causes without relying on an adult plan.